Start with what was observed
Research rarely begins as a perfectly formed query. HiDoctorly starts with a de-identified observation and helps turn it into a question the team can examine.
HiDoctorly is private validation and research infrastructure for MBBS students, MD students, practising clinicians, clinical researchers, and teams whose most valuable thinking should not become someone else’s training data.
A doctor notices a pattern between cases. A researcher finds a paper that changes the framing. A team needs to decide whether an idea is feasible before it spends a year pursuing it. Search, note-taking and drafting are usually disconnected, with no reliable record of how a claim ended up in the final document.
HiDoctorly holds that whole trajectory in one private, reviewable space. It does not replace a methodologist, an ethics committee, or a clinician's judgment. It keeps the evidence trail visible so the next decision is easier to make.
Research rarely begins as a perfectly formed query. HiDoctorly starts with a de-identified observation and helps turn it into a question the team can examine.
A useful answer is not just plausible prose. Claims remain bound to the sources that support them, with uncertainty and gaps left visible.
Owner-first isolation, a PHI gate, and controlled search egress are part of the workflow itself, not a promise added after the product is built.
HiDoctorly supports learning, research, and team-level problem solving. Students and clinicians remain responsible for interpretation, decisions, and approvals.
Independent review
Primary reviewer, research workflow and evidence integrity
Dr. Lama tested HiDoctorly as a researcher, on a real question: whether WPOI IV and WPOI V carry different prognostic weight in oral squamous cell carcinoma. He then checked the other modules against papers, references and clinical questions he could verify himself.
"A useful and thoughtfully designed platform for organising the research process, particularly from question formulation through protocol development and research governance."
What he found strongest
"HiDoctorly is strongest as a research co-pilot, workflow organiser and academic governance layer."
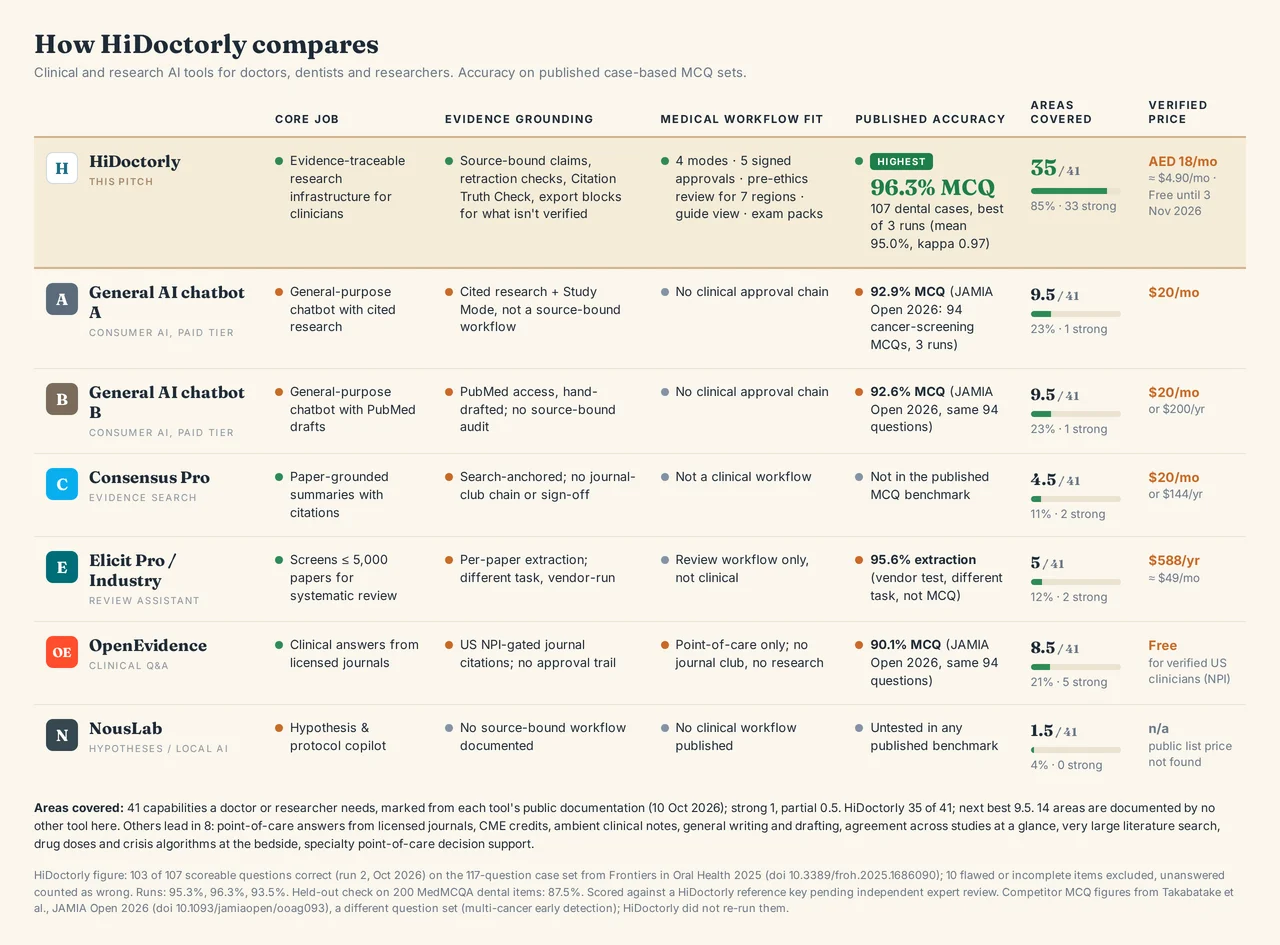
HiDoctorly answered the 117 case-based dental questions published with a 2025 study in Frontiers in Oral Health, three separate times. The same questions were used to compare general AI tools. Here is what it scored, and how.
103 of 107 case-based dental MCQs correct
Runs scored 95.3%, 96.3% and 93.5%
Fleiss kappa. Same answer in all 3 runs on 103 of 107
Unanswered counts as wrong. Only 10 flawed items excluded, listed in advance
| Tool | Core job | Evidence grounding | Medical workflow fit | Published accuracy | Areas covered out of 41 | Verified price |
|---|---|---|---|---|---|---|
HiDoctorlyThis pitch | Strong fit: Evidence-traceable research infrastructure for clinicians | Strong fit: Source-bound claims, retraction checks, Citation Truth Check, export blocks for what isn't verified | Strong fit: 4 modes · 5 signed approvals · pre-ethics review for 7 regions · guide view · exam packs | Strong fit: Highest96.3% MCQ107 dental cases, best of 3 runs (mean 95.0%, kappa 0.97) | 35 / 4185% · 33 strong | AED 18/mo≈ $4.90 · ≈ ₹472 · Free until 3 Nov 2026 |
General AI chatbot AConsumer AI, paid tier | Partial: General-purpose chatbot with cited research | Partial: Cited research + Study Mode, not a source-bound workflow | Absent or not tested: No clinical approval chain | Partial: 92.9% MCQ (JAMIA Open 2026: 94 cancer-screening MCQs, 3 runs) | 9.5 / 4123% · 1 strong | $20/mo |
General AI chatbot BConsumer AI, paid tier | Partial: General-purpose chatbot with PubMed drafts | Partial: PubMed access, hand-drafted; no source-bound audit | Absent or not tested: No clinical approval chain | Partial: 92.6% MCQ (JAMIA Open 2026, same 94 questions) | 9.5 / 4123% · 1 strong | $20/moor $200/yr |
Consensus ProEvidence search | Strong fit: Paper-grounded summaries with citations | Partial: Search-anchored; no journal-club chain or sign-off | Absent or not tested: Not a clinical workflow | Absent or not tested: Not in the published MCQ benchmark | 4.5 / 4111% · 2 strong | $20/moor $144/yr |
Elicit Pro / IndustryReview assistant | Strong fit: Screens ≤ 5,000 papers for systematic review | Partial: Per-paper extraction; different task, vendor-run | Absent or not tested: Review workflow only, not clinical | Partial: 95.6% extraction (vendor test, different task, not MCQ) | 5 / 4112% · 2 strong | $588/yr≈ $49/mo |
OpenEvidenceClinical Q&A | Strong fit: Clinical answers from licensed journals | Partial: US NPI-gated journal citations; no approval trail | Partial: Point-of-care only; no journal club, no research | Partial: 90.1% MCQ (JAMIA Open 2026, same 94 questions) | 8.5 / 4121% · 5 strong | Freefor verified US clinicians (NPI) |
NousLabHypotheses / local AI | Partial: Hypothesis & protocol copilot | Absent or not tested: No source-bound workflow documented | Absent or not tested: No clinical workflow published | Absent or not tested: Untested in any published benchmark | 1.5 / 414% · 0 strong | n/apublic list price not found |
35 of 41, strong 1 and partial 0.5
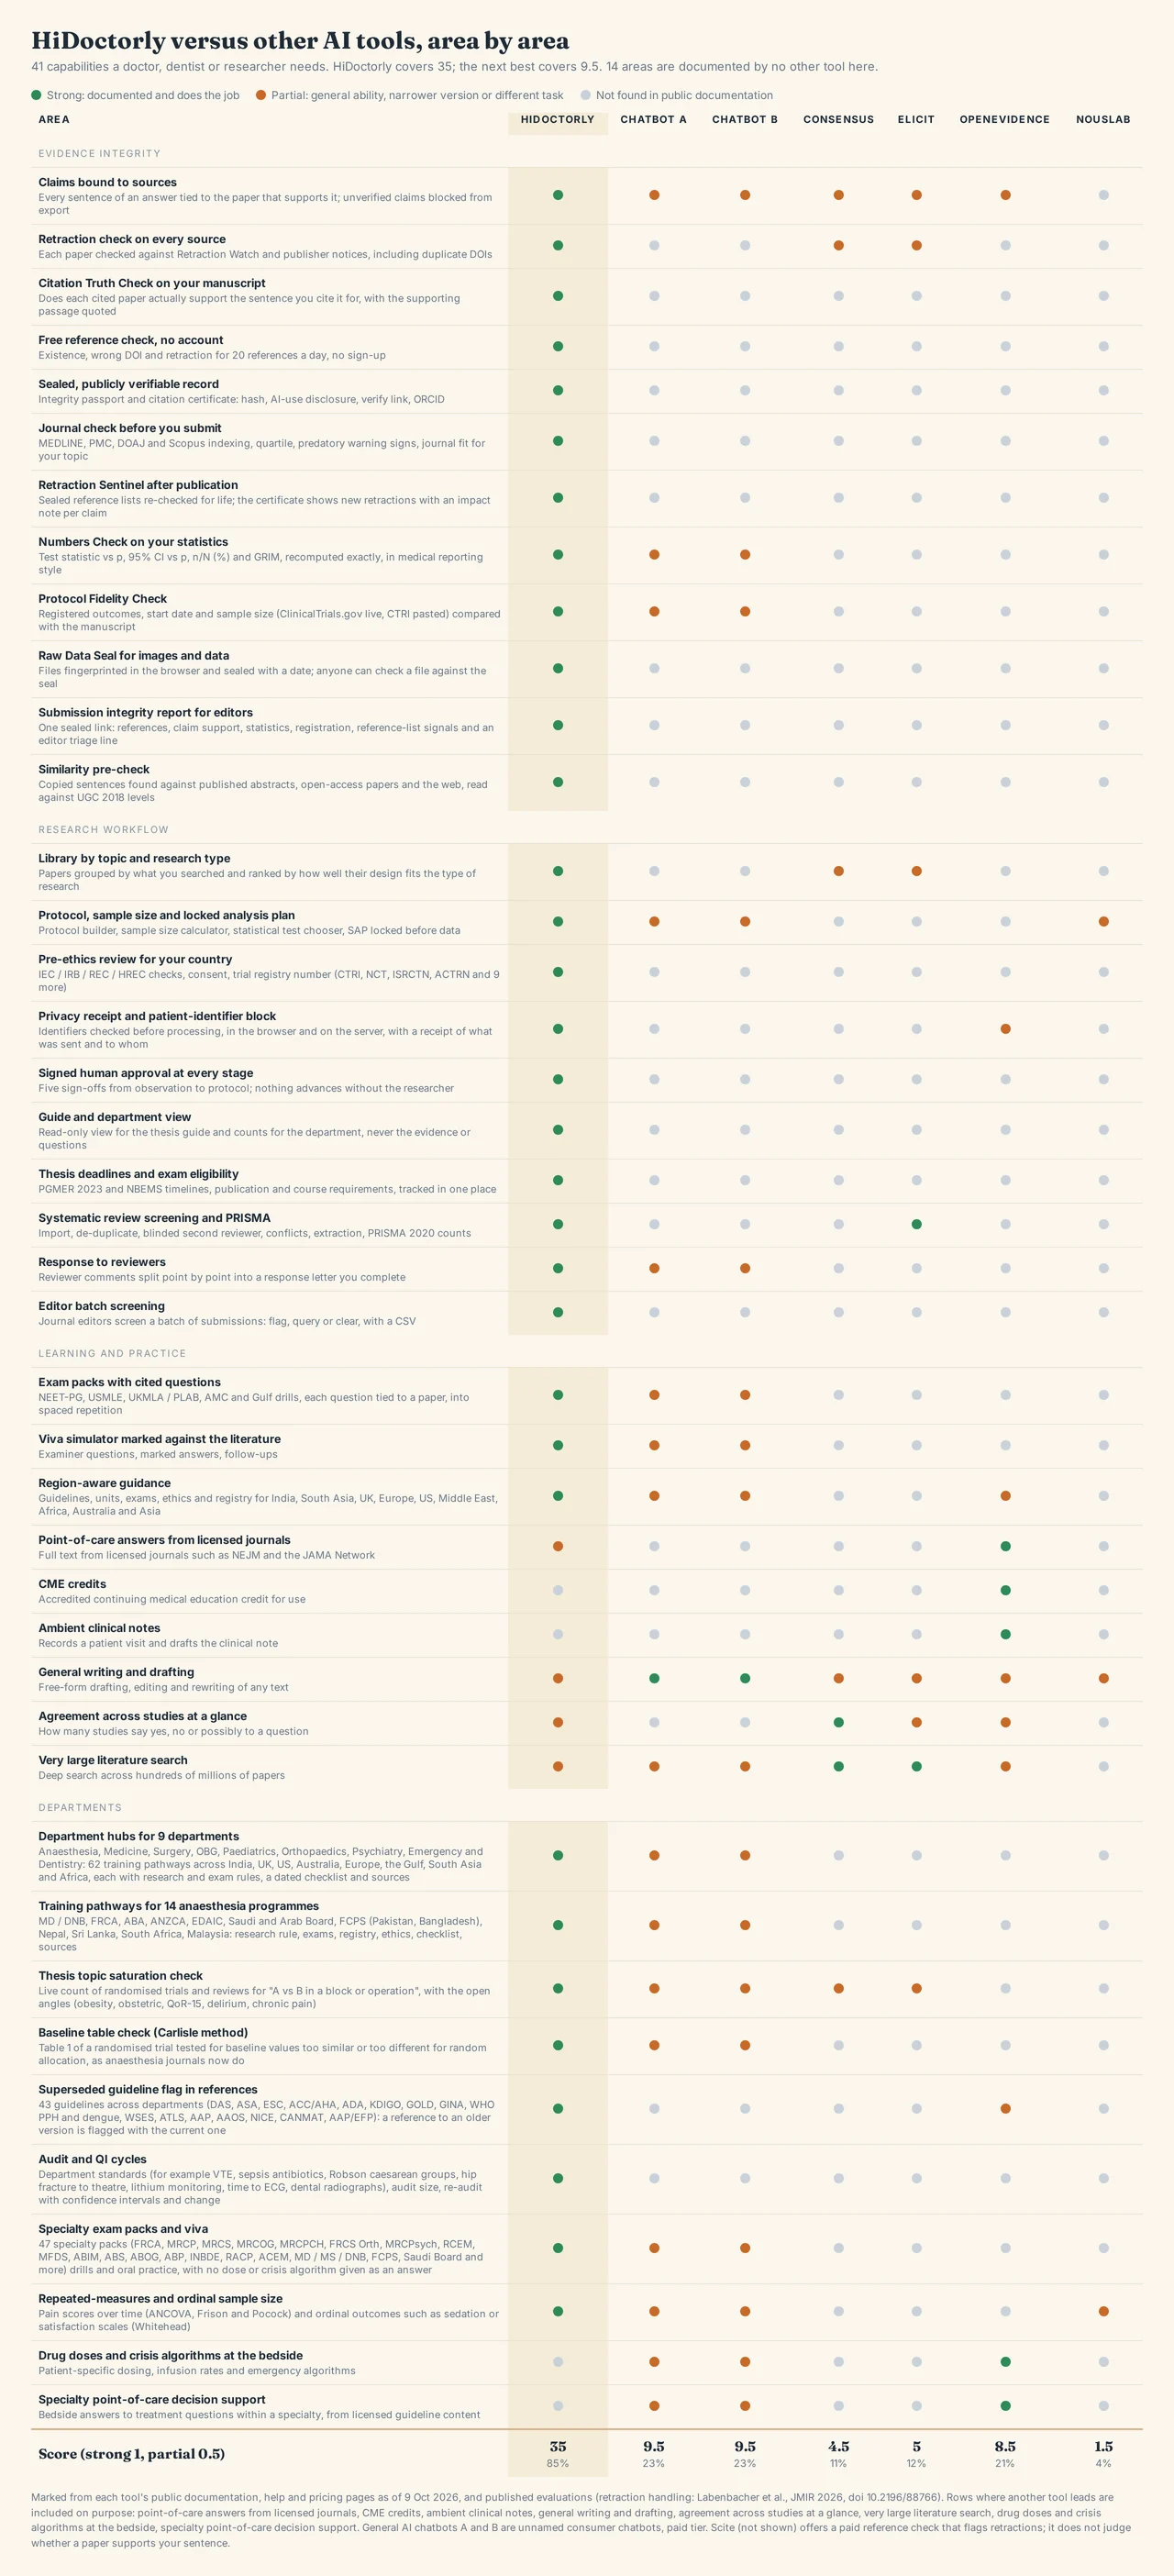
No other tool in this table documents these at all
General AI chatbot A covers 9.5
Listed below, not hidden
| Area | HiDoctorly | Chatbot A | Chatbot B | Consensus | Elicit | OpenEvidence | NousLab |
|---|---|---|---|---|---|---|---|
| Evidence integrity | |||||||
| Claims bound to sourcesEvery sentence of an answer tied to the paper that supports it; unverified claims blocked from export | Strong fit | Partial | Partial | Partial | Partial | Partial | Absent or not tested |
| Retraction check on every sourceEach paper checked against Retraction Watch and publisher notices, including duplicate DOIs A 2026 JMIR study found general and research AI tools did not reliably flag retracted papers (Labenbacher et al., doi 10.2196/88766). | Strong fit | Absent or not tested | Absent or not tested | Partial | Partial | Absent or not tested | Absent or not tested |
| Citation Truth Check on your manuscriptDoes each cited paper actually support the sentence you cite it for, with the supporting passage quoted | Strong fit | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested |
| Free reference check, no accountExistence, wrong DOI and retraction for 20 references a day, no sign-up | Strong fit | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested |
| Sealed, publicly verifiable recordIntegrity passport and citation certificate: hash, AI-use disclosure, verify link, ORCID | Strong fit | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested |
| Journal check before you submitMEDLINE, PMC, DOAJ and Scopus indexing, quartile, predatory warning signs, journal fit for your topic | Strong fit | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested |
| Retraction Sentinel after publicationSealed reference lists re-checked for life; the certificate shows new retractions with an impact note per claim Reference managers (Zotero, EndNote) warn when you cite a retracted paper in your own library; they do not watch a published work or judge the impact on its claims. | Strong fit | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested |
| Numbers Check on your statisticsTest statistic vs p, 95% CI vs p, n/N (%) and GRIM, recomputed exactly, in medical reporting style A general chatbot can recompute a p-value when asked, one at a time; it does not scan a manuscript. | Strong fit | Partial | Partial | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested |
| Protocol Fidelity CheckRegistered outcomes, start date and sample size (ClinicalTrials.gov live, CTRI pasted) compared with the manuscript A general chatbot can compare two pasted texts; it does not read the registry or check registration timing. | Strong fit | Partial | Partial | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested |
| Raw Data Seal for images and dataFiles fingerprinted in the browser and sealed with a date; anyone can check a file against the seal | Strong fit | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested |
| Submission integrity report for editorsOne sealed link: references, claim support, statistics, registration, reference-list signals and an editor triage line | Strong fit | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested |
| Similarity pre-checkCopied sentences found against published abstracts, open-access papers and the web, read against UGC 2018 levels | Strong fit | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested |
| Research workflow | |||||||
| Library by topic and research typePapers grouped by what you searched and ranked by how well their design fits the type of research | Strong fit | Absent or not tested | Absent or not tested | Partial | Partial | Absent or not tested | Absent or not tested |
| Protocol, sample size and locked analysis planProtocol builder, sample size calculator, statistical test chooser, SAP locked before data | Strong fit | Partial | Partial | Absent or not tested | Absent or not tested | Absent or not tested | Partial |
| Pre-ethics review for your countryIEC / IRB / REC / HREC checks, consent, trial registry number (CTRI, NCT, ISRCTN, ACTRN and 9 more) | Strong fit | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested |
| Privacy receipt and patient-identifier blockIdentifiers checked before processing, in the browser and on the server, with a receipt of what was sent and to whom OpenEvidence offers HIPAA-compliant handling for US clinicians; it does not show a per-request receipt. | Strong fit | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested | Partial | Absent or not tested |
| Signed human approval at every stageFive sign-offs from observation to protocol; nothing advances without the researcher | Strong fit | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested |
| Guide and department viewRead-only view for the thesis guide and counts for the department, never the evidence or questions | Strong fit | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested |
| Thesis deadlines and exam eligibilityPGMER 2023 and NBEMS timelines, publication and course requirements, tracked in one place | Strong fit | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested |
| Systematic review screening and PRISMAImport, de-duplicate, blinded second reviewer, conflicts, extraction, PRISMA 2020 counts Elicit screens at larger scale (up to 5,000 papers on Pro). | Strong fit | Absent or not tested | Absent or not tested | Absent or not tested | Strong fit | Absent or not tested | Absent or not tested |
| Response to reviewersReviewer comments split point by point into a response letter you complete | Strong fit | Partial | Partial | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested |
| Editor batch screeningJournal editors screen a batch of submissions: flag, query or clear, with a CSV | Strong fit | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested |
| Learning and practice | |||||||
| Exam packs with cited questionsNEET-PG, USMLE, UKMLA / PLAB, AMC and Gulf drills, each question tied to a paper, into spaced repetition | Strong fit | Partial | Partial | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested |
| Viva simulator marked against the literatureExaminer questions, marked answers, follow-ups | Strong fit | Partial | Partial | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested |
| Region-aware guidanceGuidelines, units, exams, ethics and registry for India, South Asia, UK, Europe, US, Middle East, Africa, Australia and Asia | Strong fit | Partial | Partial | Absent or not tested | Absent or not tested | Partial | Absent or not tested |
| Point-of-care answers from licensed journalsFull text from licensed journals such as NEJM and the JAMA Network OpenEvidence licenses NEJM and JAMA content; HiDoctorly uses open-access full text only. | Partial | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested | Strong fit | Absent or not tested |
| CME creditsAccredited continuing medical education credit for use OpenEvidence offers AMA PRA Category 1 credit to US clinicians. | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested | Strong fit | Absent or not tested |
| Ambient clinical notesRecords a patient visit and drafts the clinical note OpenEvidence Visits. | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested | Strong fit | Absent or not tested |
| General writing and draftingFree-form drafting, editing and rewriting of any text HiDoctorly drafts within research stages; general chatbots draft anything. | Partial | Strong fit | Strong fit | Partial | Partial | Partial | Partial |
| Agreement across studies at a glanceHow many studies say yes, no or possibly to a question Consensus Meter; HiDoctorly shows a certainty profile and evidence levels instead. | Partial | Absent or not tested | Absent or not tested | Strong fit | Partial | Partial | Absent or not tested |
| Very large literature searchDeep search across hundreds of millions of papers Consensus searches over 200 million papers; HiDoctorly searches PubMed, Europe PMC, Crossref and OpenAlex per question. | Partial | Partial | Partial | Strong fit | Strong fit | Partial | Absent or not tested |
| Departments | |||||||
| Department hubs for 9 departmentsAnaesthesia, Medicine, Surgery, OBG, Paediatrics, Orthopaedics, Psychiatry, Emergency and Dentistry: 62 training pathways across India, UK, US, Australia, Europe, the Gulf, South Asia and Africa, each with research and exam rules, a dated checklist and sources General chatbots can describe a pathway from memory; they do not keep a sourced, dated checklist per department. | Strong fit | Partial | Partial | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested |
| Training pathways for 14 anaesthesia programmesMD / DNB, FRCA, ABA, ANZCA, EDAIC, Saudi and Arab Board, FCPS (Pakistan, Bangladesh), Nepal, Sri Lanka, South Africa, Malaysia: research rule, exams, registry, ethics, checklist, sources General chatbots can describe a pathway from memory; they do not keep a sourced, dated checklist. | Strong fit | Partial | Partial | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested |
| Thesis topic saturation checkLive count of randomised trials and reviews for "A vs B in a block or operation", with the open angles (obesity, obstetric, QoR-15, delirium, chronic pain) Consensus and Elicit return papers on a topic; they do not count trials against reviews or suggest the uncovered angle. | Strong fit | Partial | Partial | Partial | Partial | Absent or not tested | Absent or not tested |
| Baseline table check (Carlisle method)Table 1 of a randomised trial tested for baseline values too similar or too different for random allocation, as anaesthesia journals now do A chatbot with code can run the test if you write it; none offers it as a check. | Strong fit | Partial | Partial | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested |
| Superseded guideline flag in references43 guidelines across departments (DAS, ASA, ESC, ACC/AHA, ADA, KDIGO, GOLD, GINA, WHO PPH and dengue, WSES, ATLS, AAP, AAOS, NICE, CANMAT, AAP/EFP): a reference to an older version is flagged with the current one OpenEvidence answers from current guidelines; it does not check your reference list. | Strong fit | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested | Partial | Absent or not tested |
| Audit and QI cyclesDepartment standards (for example VTE, sepsis antibiotics, Robson caesarean groups, hip fracture to theatre, lithium monitoring, time to ECG, dental radiographs), audit size, re-audit with confidence intervals and change | Strong fit | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested |
| Specialty exam packs and viva47 specialty packs (FRCA, MRCP, MRCS, MRCOG, MRCPCH, FRCS Orth, MRCPsych, RCEM, MFDS, ABIM, ABS, ABOG, ABP, INBDE, RACP, ACEM, MD / MS / DNB, FCPS, Saudi Board and more) drills and oral practice, with no dose or crisis algorithm given as an answer | Strong fit | Partial | Partial | Absent or not tested | Absent or not tested | Absent or not tested | Absent or not tested |
| Repeated-measures and ordinal sample sizePain scores over time (ANCOVA, Frison and Pocock) and ordinal outcomes such as sedation or satisfaction scales (Whitehead) | Strong fit | Partial | Partial | Absent or not tested | Absent or not tested | Absent or not tested | Partial |
| Drug doses and crisis algorithms at the bedsidePatient-specific dosing, infusion rates and emergency algorithms HiDoctorly does not give doses or algorithms by design; OpenEvidence answers clinical dosing questions for clinicians. | Absent or not tested | Partial | Partial | Absent or not tested | Absent or not tested | Strong fit | Absent or not tested |
| Specialty point-of-care decision supportBedside answers to treatment questions within a specialty, from licensed guideline content HiDoctorly supports training and research, not bedside treatment decisions; OpenEvidence answers clinical questions for clinicians. | Absent or not tested | Partial | Partial | Absent or not tested | Absent or not tested | Strong fit | Absent or not tested |
| Score | 35 | 9.5 | 9.5 | 4.5 | 5 | 8.5 | 1.5 |
Marked from each tool's public documentation, help and pricing pages as of 10 Oct 2026, and the published evaluations cited. Strong = documented and does the job; partial = general ability, a narrower version or a different task; absent = not found in public documentation. Score: strong 1, partial 0.5. Rows where another tool leads are included. Scite (not in this table) offers a paid reference check that flags retractions and shows how each reference is cited elsewhere; it does not judge whether a paper supports your sentence. Download the matrix as an image
Answers are bound to the papers that support them, checked against retraction notices, and exports are blocked for anything that is not verified.
Five signed approvals and an Integrity Passport show how AI was used in your thesis, with a public verification link.
Protocol within 180 days, thesis by month 26, journal and similarity pre-checks before you submit.
AED 18 (about $4.90 / ₹472) a month, free until 3 Nov 2026. General AI tools listed above start at $20 (about ₹1,930) a month.
Whether the work is a student’s difficult concept, a resident’s research question, a clinician’s unanswered observation, or an institution’s research program, HiDoctorly keeps the owner, the evidence, and the validation trail in view.
Build sound foundations, compare sources, and validate your understanding privately before a viva, case discussion, or journal club.
Move from clinical observations to evidence review, critical appraisal, and a feasible protocol with a traceable chain of reasoning.
Validate research questions, workflow problems, and evidence privately with clear ownership, auditability, and controlled egress.

In August 2026 Satyavrat Nirala and Naveen Babu Garikapati launched HiMirrorly, a self-limiting “honest mirror” built on the HI > EI > AI idea: human judgement first, machines never making the final decision. Indian media carried it in English and Hindi. HiDoctorly, from the same creators, brings that conviction to medical evidence: you observe, the evidence is checked, and you decide.
Coverage is of HiMirrorly, our earlier product. Logos identify the outlets and do not imply endorsement.
HiDoctorly does not diagnose, prescribe, dose, or issue patient-specific emergency instructions. It frames problems, retrieves evidence, compares options, and leaves the human decision-maker with a trace they can review.
© 2026 Satyavrat Nirala · HiDoctorly